

“Doctor, how often does it go wrong?” Almost everyone who sits in front of me considering zygomatic implants asks this sooner or later, usually after being told, somewhere else, that there is not enough bone for conventional implants. It is a fair question, and I would rather answer it with numbers than with reassurance.
In this text I go through what the largest reviews report on success, failure and complications, why two of them disagree on the sinus, what the studies cannot tell you, and what I actually do to keep your own risk as low as it can be. If you are looking at this from outside Brazil, the questions at the end work for any clinic you are considering, mine included.
Quick answer: in a 2023 meta-analysis of 18 studies, zygomatic implants had a survival of 96.2% at six years, with sinusitis the most frequent complication (14.2% at five years). An older review reported lower sinusitis rates (2.4%), but the authors themselves said this was probably underestimated. Most failures happen early, in the first months. The reviews average many surgeons and many cases, so they describe what is typical, not what will happen to you. Your own result depends mostly on the tomography, the planning, the surgeon’s experience with this specific technique and the follow-up afterwards.

What the largest reviews report
Three systematic reviews give the clearest picture, and they measure slightly different things, so I will keep them apart.
A 2023 systematic review and meta-analysis included 18 studies, with 1,349 zygomatic implants in 623 patients, followed for 75.4 months on average (from 3 to almost 12 years). Implant survival was 96.2% at six years, and the annual rate of failure was 0.7%. When the prosthesis was loaded immediately, survival was 98.1%, against 95% when loading was delayed, a statistically significant difference. Prosthesis survival was 94%. The authors concluded that long-term survival is comparable to conventional implants, and that sinusitis was the biological complication seen most often [1].
An earlier review, from 2016, pooled 68 studies, with 4,556 zygomatic implants in 2,161 patients and 103 failures. The cumulative survival at 12 years was 95.21%, and most failures were detected within the first six months after surgery. Complications were reported as sinusitis 2.4%, soft tissue infection 2.0%, paresthesia 1.0% and oroantral fistula 0.4%, with a warning that these figures may be underestimated because many studies did not report them [2]. A still earlier review by the same group, in 2012, found a 12-year survival of 96.7% in 42 studies and added a sentence I agree with: placing zygomatic implants requires very experienced surgeons, because delicate structures are nearby [3].
A 2021 meta-analysis of 46 studies (32 of them in the quantitative analysis) compared failures between the two kinds of implants: 0.69% for zygomatic implants and 2.89% for conventional ones, with prosthetic complications in 4.9% and sinus complications in 4.7% [4]. Keep in mind that the two kinds of implants were placed in different patients and different starting conditions, so I do not read this as “zygomatic is safer”. I read it as “zygomatic is not an unreasonable choice when the bone is truly gone”.

Why the sinus numbers do not match
You will have noticed that sinusitis appears as 2.4%, 4.7% and 14.2%. This is not a typo, and it is not a contradiction I can resolve for you. The studies define sinusitis differently, follow patients for different lengths of time, and some do not report it at all. The 14.2% comes from a review that looked at prevalence at five years, which captures the problems that appear late. The 2016 authors state that sinusitis “can appear several years after” the surgery, which is why I do not stop watching it when the prosthesis is delivered.
In practice, this is how I explain it to patients: expect the sinus to be the thing we follow most closely, plan for it, and tell me early if you notice nasal blockage, pressure, or a change in how you breathe on one side. Most cases of sinus inflammation are handled with medication. The numbers say that some are not, and I would rather you hear that from me now.
What the studies do not tell you
A systematic review of 33 studies on severely atrophic maxillae, published in 2023, could not even pool the results, because the studies were too different from each other. Its authors concluded that a single approach cannot be recommended as the gold standard, that the choice depends on the patient’s biology and on the clinician’s expertise, and that the quality of evidence was low to medium [5]. That is the honest ceiling of the literature today.
Other limits are worth knowing:
- Most of the studies are observational. Randomized trials comparing zygomatic implants with other treatments are few.
- The reviews average many surgeons. They cannot say how a given team performs.
- Patients who had part of the jaw removed because of a tumor had lower survival in the reviews, so those results should not be read as applying to the usual patient with bone loss from long-term tooth loss [2,3].
- Follow-up is rarely beyond 10 years, and complications are not always reported.
What shapes your own result
If the averages cannot tell you your outcome, what can? In my experience, and in what the reviews suggest, these are the factors that matter most:
- The tomography and the planning. I ask for the tomography and show it on the screen, so you can see where the bone is and where it is not. The path of each implant is planned before the day of surgery.
- The surgeon’s training with this specific technique. It has a steeper learning curve than conventional implants, and the literature says so [3]. Ask how many cases the person has done, and do not be offended if I am asked the same.
- Your general health. As with every surgical patient, I ask for the surgical risk report from your cardiologist and laboratory tests (glycated hemoglobin, fasting glucose, blood count and coagulation tests). Conditions like uncontrolled diabetes change the plan.
- Smoking and daily hygiene. They affect healing and the long-term health of the tissues around the implants.
- Follow-up. I schedule your returns closer together than for a conventional case, and the visits continue after the prosthesis is delivered.
How I handle it in practice
Some patients need four zygomatic implants, and others need two zygomatic implants with conventional ones in front. The tomography decides, not my preference. When there is sedation, it is always given by the anesthesiologist, who also releases you after the recovery period. Sedation is not done without a companion. In some zygomatic cases, general anesthesia is the better choice, and we talk about it beforehand.
Decisions about surgery are made in person, with the scan open in front of both of us. If someone shares the decision with you, a spouse or a son or daughter, I ask that they come to the consultation too, because it is not a decision to be made through a message.
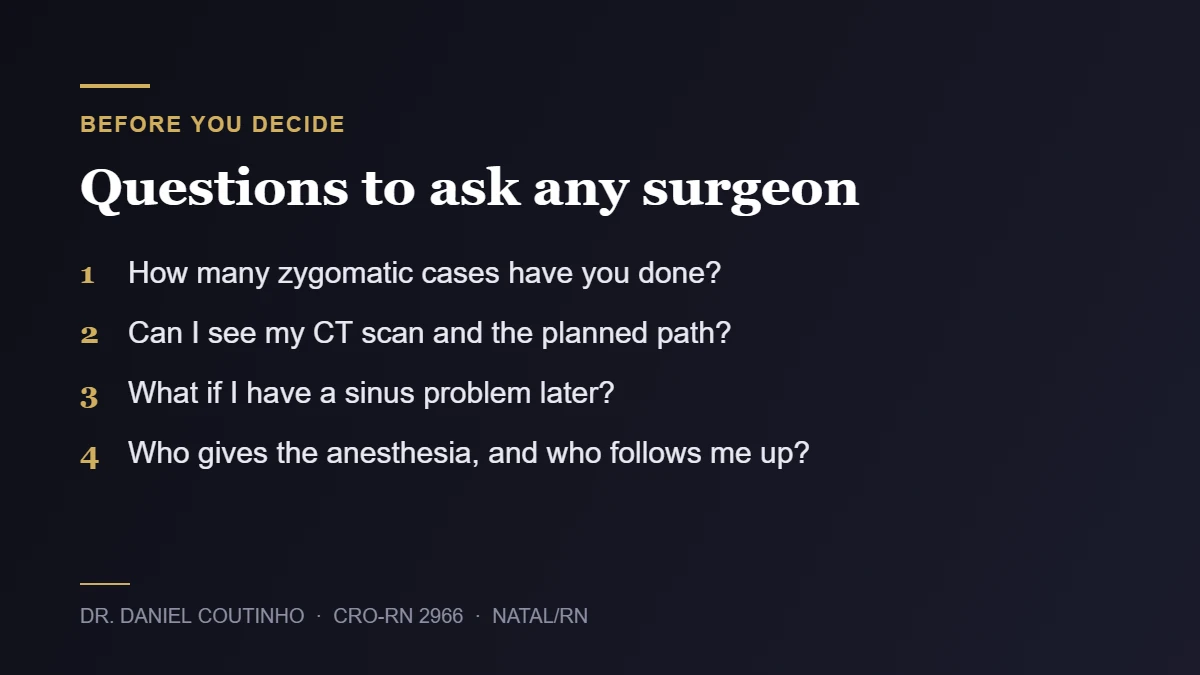
Questions worth asking any surgeon
- How many zygomatic cases have you personally performed, and with what follow-up?
- Can I see my tomography, and where is the bone you are planning to use?
- What is the plan if I develop a sinus problem two years from now?
- Who gives the sedation or anesthesia, and where is the surgery done?
- Who looks after me after the prosthesis is delivered, and for how long?
What the evidence allows us to say, and what it does not
It allows us to say that zygomatic implants have high survival in the studies we have, in the range of 95% to 96% over six to twelve years, that failures are mostly early, and that sinusitis is the complication to plan for [1,2,4]. It does not allow us to say that the result is the same in every hand, that no other approach can work, or that you will not have a complication. The honest reading is a technique with solid numbers, uneven studies, and a dependence on who plans and places it.
Are zygomatic implants safe?
In the reviews, survival at six to twelve years is in the range of 95% to 96%. The surgery is more demanding than conventional implants, and safety depends on planning, the surgeon’s experience and follow-up.
What is the failure rate of zygomatic implants?
In a 2023 meta-analysis, the annual failure rate was 0.7%, with survival of 96.2% at six years. In a 2016 review, most failures occurred in the first six months.
Can zygomatic implants affect the sinus?
Yes. Sinusitis is the most commonly reported biological complication. Reported rates range from 2.4% to 14.2% depending on how it is defined and how long patients are followed, so the sinus needs long-term attention.
Does surgeon experience change the outcome?
The reviews state that the technique requires very experienced surgeons and has a steeper learning curve. How much experience changes your individual result is not something the studies measured precisely.
What happens if a zygomatic implant fails?
It depends on the case: which implant, when, and why. It is part of the plan I discuss before surgery, including what follow-up and what options exist.
Sources
- [1] Brennand Roper M, et al. Long-term treatment outcomes with zygomatic implants: a systematic review and meta-analysis. Int J Implant Dent. 2023;9(1):21. doi:10.1186/s40729-023-00479-x
- [2] Chrcanovic BR, Albrektsson T, Wennerberg A. Survival and complications of zygomatic implants: an updated systematic review. J Oral Maxillofac Surg. 2016;74(10):1949-1964. doi:10.1016/j.joms.2016.06.166
- [3] Chrcanovic BR, Abreu MHNG. Survival and complications of zygomatic implants: a systematic review. Oral Maxillofac Surg. 2013;17(2):81-93. doi:10.1007/s10006-012-0331-z
- [4] Gutiérrez Muñoz D, et al. Survival rate and prosthetic and sinus complications of zygomatic dental implants for the rehabilitation of the atrophic edentulous maxilla: a systematic review and meta-analysis. Biology (Basel). 2021;10(7):601. doi:10.3390/biology10070601
- [5] Alsi SA, Deshpande S, Pande N. Clinical outcomes of implant-supported prosthetic rehabilitation of severely atrophic maxilla: a systematic review. J Indian Prosthodont Soc. 2023;23(4):335-346. doi:10.4103/jips.jips_360_23
Book your first consultation in Natal, Brazil
If you are considering zygomatic implants and want a clear opinion on your case, the first step is a consultation with Dr. Daniel Coutinho (CRO-RN 2966), in Natal. Send your CT scan if you have one, and tell us what you were told elsewhere. We will say honestly whether your case fits this technique or not.
Cartas do Dr. Daniel Coutinho. Uma carta a cada 15 dias com um assunto como este, explicado com calma. Sem propaganda; para sair, é só responder SAIR.